
Quick answer: bppv vs meniere disease should be judged by the full symptom pattern, not by one isolated phrase. This updated guide explains what the symptom may mean, when routine clinic review is enough, and which warning signs need urgent care.
What this page helps you understand
Use this page to connect your symptoms with the right care pathway, the main vertigo hub, the most relevant DRP guides, and the details worth telling the doctor.
Reviewed by Dr. Prateek Porwal, MBBS, DNB ENT, CAMVD. Dr. Porwal evaluates Meniere disease, vertigo, tinnitus, hearing fluctuation, VNG findings and balance disorders at Prime ENT Center, Hardoi.
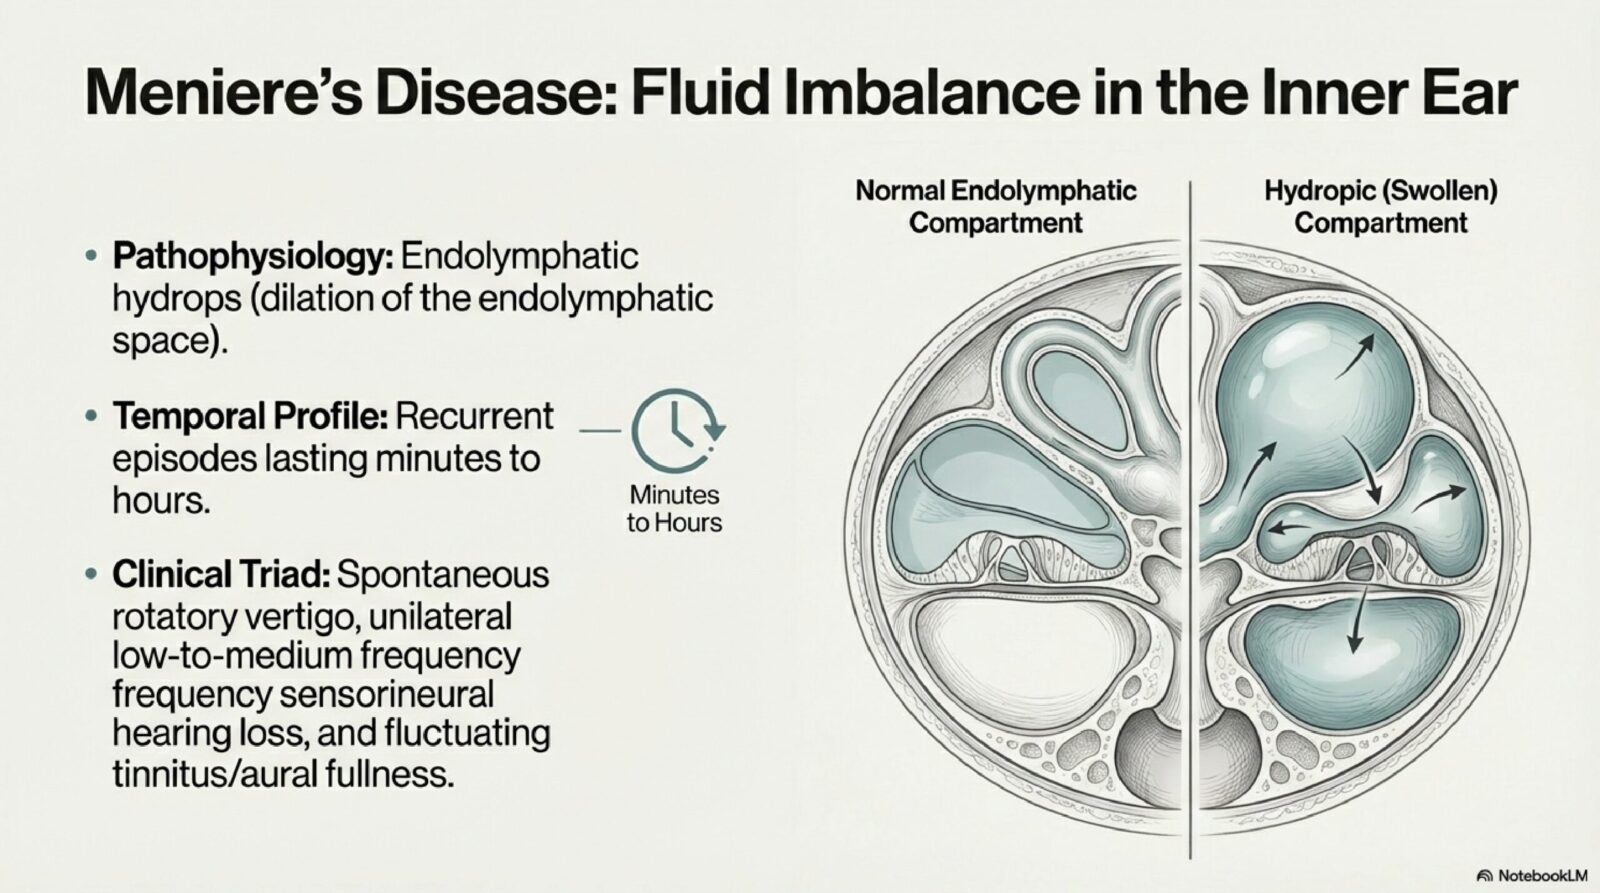
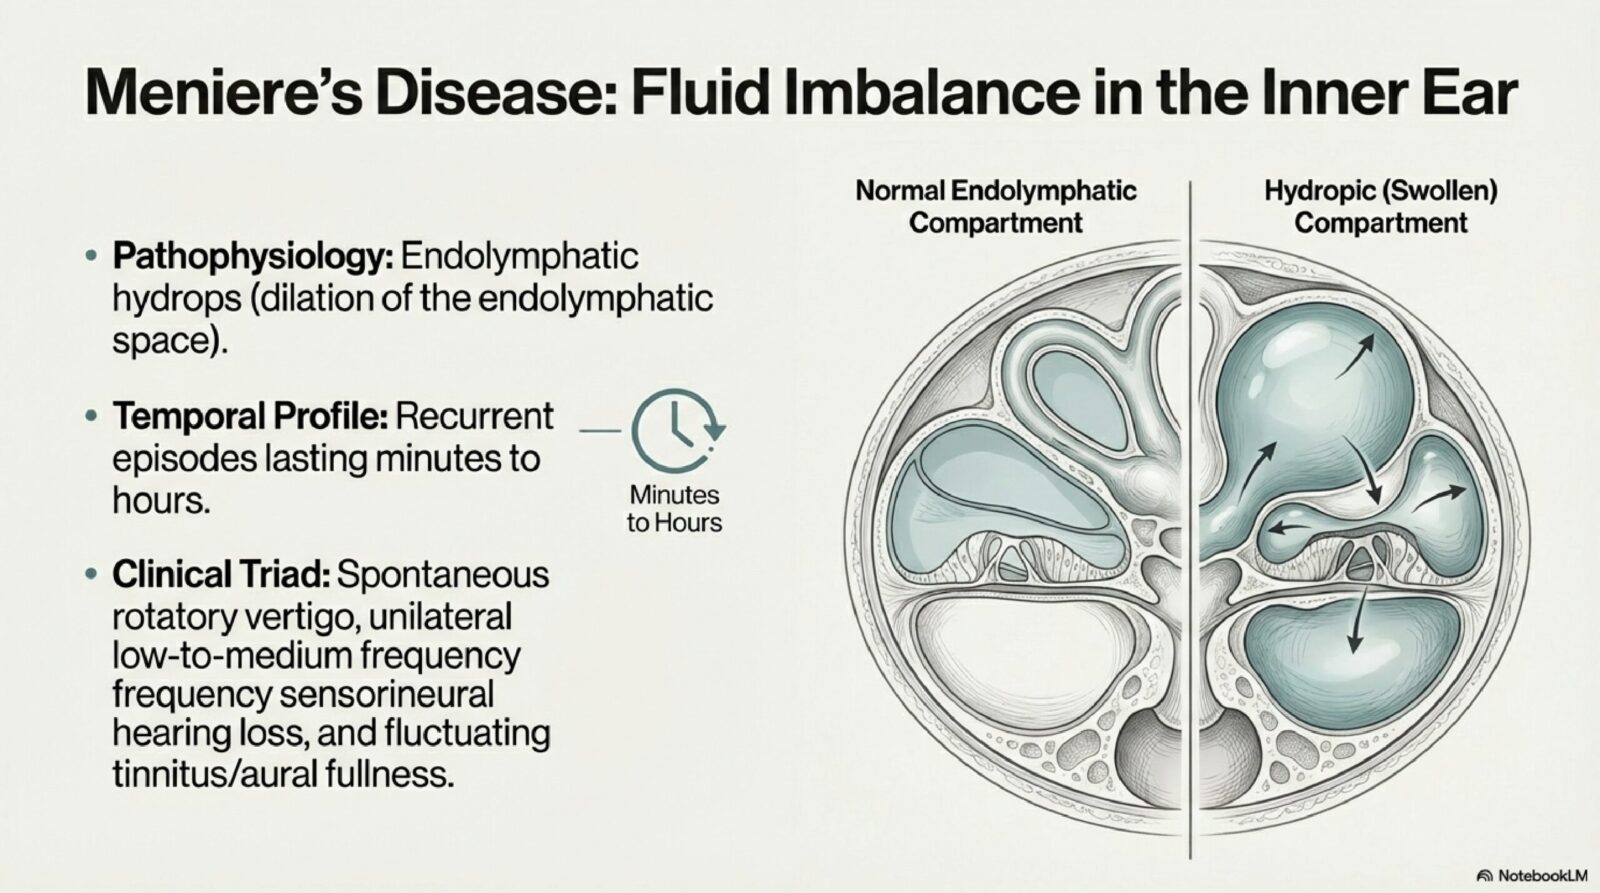
meniere vs bppv is part of a Meniere disease evaluation. The main question is whether vertigo attacks, tinnitus, ear fullness and hearing changes fit the same ear-focused pattern, or whether another diagnosis explains the symptoms better.
BPPV vs Meniere disease: quick answer
Meniere vs BPPV matters because the treatments are different. BPPV is a canal crystal problem that usually causes brief position-triggered spinning. Meniere disease causes longer spontaneous vertigo attacks with ear fullness, tinnitus and hearing fluctuation.
Why this topic matters
BPPV attacks usually last seconds to under a minute after rolling in bed, looking up or bending. Meniere attacks classically last 20 minutes to 12 hours and are not explained by a single head position. Meniere also needs hearing assessment because low-frequency sensorineural hearing loss supports the diagnosis.
How I check this in clinic
I compare the story with Dix-Hallpike, roll test, audiogram and nystagmus pattern. A patient may have both disorders, so a positive positional test does not automatically explain every longer attack with tinnitus.
What tests may be needed
Audiogram is usually the first anchor test because Meniere disease is linked with sensorineural hearing change. Depending on the case, VNG, vHIT, VEMP, MRI, blood pressure review or migraine screening may be needed. The AAO-HNS guideline also emphasizes checking for vestibular migraine when assessing suspected Meniere disease.
Red flags
Red flags include new neurological symptoms, severe gait ataxia, fainting, sudden hearing loss, persistent vertical nystagmus, or attacks that do not fit either BPPV or Meniere disease. These patients need broader assessment.
Treatment direction
BPPV treatment is canalith repositioning. Meniere management may include diet and fluid planning, attack medicines, hearing monitoring, betahistine or diuretics, vestibular rehab for chronic imbalance, and escalation when attacks remain disabling.
How it connects to the Meniere silo
Read the main Meniere disease guide first if you need the full overview. For attack pattern comparison, use Meniere vs vestibular migraine after this page. For testing, use the vertigo diagnosis guide and VNG testing guide.
If hearing is already poor or attacks remain disabling despite noninvasive care, treatment conversations may move toward intratympanic steroids, gentamicin or surgery. Those decisions should be based on attack severity, hearing status, daily risk and patient goals.
What patients should track
Keep an attack diary that records date, start time, duration, ear fullness, tinnitus side, hearing change, nausea, headache, visual symptoms, salt-heavy meals, sleep, stress, medicines taken and recovery time. Bring old audiograms because hearing trend is more useful than a single report.
Common mistakes
Do not diagnose Meniere disease from dizziness alone. Do not keep repeating Epley maneuvers for long spontaneous attacks with hearing fluctuation. Do not ignore migraine features. Do not start strict salt restriction or diuretics without considering blood pressure, kidney status and other medicines.
How follow-up changes the diagnosis
Meniere disease often becomes clearer over time. A first visit may only show probable disease, because hearing can fluctuate and the patient may arrive between attacks. Repeating audiograms, comparing the affected ear with the other ear, and documenting whether tinnitus or fullness appears before vertigo can prevent both overdiagnosis and missed diagnosis.
Follow-up also protects patients from the wrong treatment path. A patient whose attacks shorten to seconds may need positional testing for BPPV. A patient with headache, light sensitivity and motion sensitivity may need migraine care. A patient with progressive asymmetric hearing loss may need imaging or broader ear evaluation. The label should follow the evidence, not the other way around.
Safety and daily planning
During active Meniere disease, patients should think practically about safety. Avoid driving during an attack, avoid ladders and heights when attacks are unpredictable, sit or lie down when ear pressure and spinning begin, and tell family members what symptoms mean emergency care. Older patients and patients living alone need a fall plan.
The goal is not to make the patient afraid of normal life. The goal is to match risk to the pattern. Someone with rare mild attacks needs reassurance and monitoring. Someone with vomiting, falls, drop attacks or poor hearing needs a more structured plan and faster escalation.
FAQ
Can Meniere vs BPPV be diagnosed online?
No. Online information can help you prepare questions, but Meniere disease decisions need history, ear examination, audiogram and sometimes vestibular testing or imaging.
Is Meniere disease curable?
There is no guaranteed cure. Many patients can reduce attack burden and improve safety with staged care, but hearing and balance need follow-up over time.
Bppv vs meniere disease: first choose the right path
Seek urgent care for weakness, slurred speech, double vision, severe new headache, fainting, chest pain, sudden hearing loss, repeated vomiting with dehydration, a serious fall, facial weakness with eye exposure, or inability to walk safely. Book routine review when symptoms are recurrent, confusing, not improving, or affecting work, sleep, travel or confidence.
Helpful next pages
What to tell the doctor
Write when the problem started, what triggers it, how long it lasts, whether hearing, headache, vision, walking, fainting, vomiting, facial weakness or falls are involved, and which medicines, maneuvers or previous reports you already have.
BPPV vs Meniere disease: symptom pattern checklist
When patients compare BPPV vs Meniere disease, the most useful detail is the pattern of each attack. BPPV usually gives a short spinning burst after turning in bed, looking up, bending, or changing head position. The spinning may be intense, but it often settles within seconds to a minute once the head stays still. Between attacks, many patients feel cautious or mildly off-balance, but hearing is usually unchanged.
Meniere disease behaves differently. Attacks often last longer, may come with ear fullness, ringing, fluctuating hearing, nausea, and a washed-out feeling after the episode. Some patients describe pressure in one ear before the vertigo starts. If the story includes hearing change, tinnitus, or repeated longer attacks, it should not be treated as simple positional vertigo without checking the ear and hearing.
What can confuse the diagnosis?
BPPV and Meniere disease can overlap with vestibular migraine, labyrinthitis, vestibular neuritis, anxiety-related dizziness, and blood-pressure symptoms. A patient may also have BPPV after another inner-ear illness. This is why one internet label is not enough. The doctor needs attack duration, trigger, ear symptoms, headache pattern, walking safety, medicines, and previous test reports.
When testing is helpful
Positional testing such as Dix-Hallpike helps when attacks are triggered by head movement. Hearing tests help when tinnitus, fullness, or hearing fluctuation is present. VNG or other balance tests may be useful when the history is mixed, treatment is not working, or more than one vestibular problem is possible. The safest plan is to match treatment to the pattern rather than repeating random maneuvers or medicines.
How treatment direction changes after the diagnosis
If the final diagnosis is BPPV, treatment usually focuses on identifying the affected canal and using the correct repositioning maneuver. Medicines may reduce nausea for a short time, but they do not move the crystals back. If the final diagnosis is Meniere disease, the discussion is different: hearing tests, salt and fluid pattern, migraine overlap, attack prevention, rescue medicines, and sometimes intratympanic treatment may be considered.
This is why a patient should avoid doing repeated random Epley maneuvers for every vertigo attack. If attacks are lasting hours, linked with ear pressure, or followed by hearing fluctuation, the treatment path should be reviewed. If attacks are always brief and triggered by turning in bed, positional testing becomes more important. A clear diagnosis saves time and prevents unnecessary medicines.
Questions to bring for BPPV vs Meniere disease review
Before the visit, note whether attacks are seconds, minutes, or hours; whether they start with turning in bed; whether one ear feels blocked; whether tinnitus becomes louder; and whether hearing changes after the attack. Ask which diagnosis best fits the timeline, whether a hearing test is needed, whether a maneuver is appropriate, and what to do if the next attack is different. This makes the consultation more useful and reduces trial-and-error treatment.
Follow-up plan after the first visit
After the first visit, follow the diagnosis-specific plan and record the next two or three attacks. If a maneuver helps but symptoms return, note which side or position triggered it. If hearing changes, repeat hearing evaluation may be needed. If symptoms shift from brief positional spinning to longer attacks with ear pressure, the diagnosis may need review. Follow-up is especially important when treatment response does not match the expected pattern.
References
AAO-HNS Clinical Practice Guideline: Meniere’s Disease key action statements: AAO-HNS Meniere disease clinical guideline summary
NIDCD. Meniere’s Disease diagnosis and treatment: https://www.nidcd.nih.gov/health/menieres-disease
Merck Manual Professional. Meniere Disease: Merck Manual professional Meniere disease overview
Tumarkin/drop attacks in Meniere disease, PubMed: BPPV clinical guideline reference
For non-emergency Meniere disease, vertigo, tinnitus, hearing fluctuation or VNG evaluation, book an appointment or call/WhatsApp 7393062200. Sudden weakness, double vision, slurred speech, severe headache, fainting or inability to walk needs urgent care first.
Medical disclaimer: This article is for educational purpose and patient education. Meniere disease can resemble vestibular migraine, BPPV and central vertigo. Diagnosis and treatment should be individualized after ENT evaluation and hearing testing.